Tuesday, December 16, 2014
Wednesday, May 7, 2014
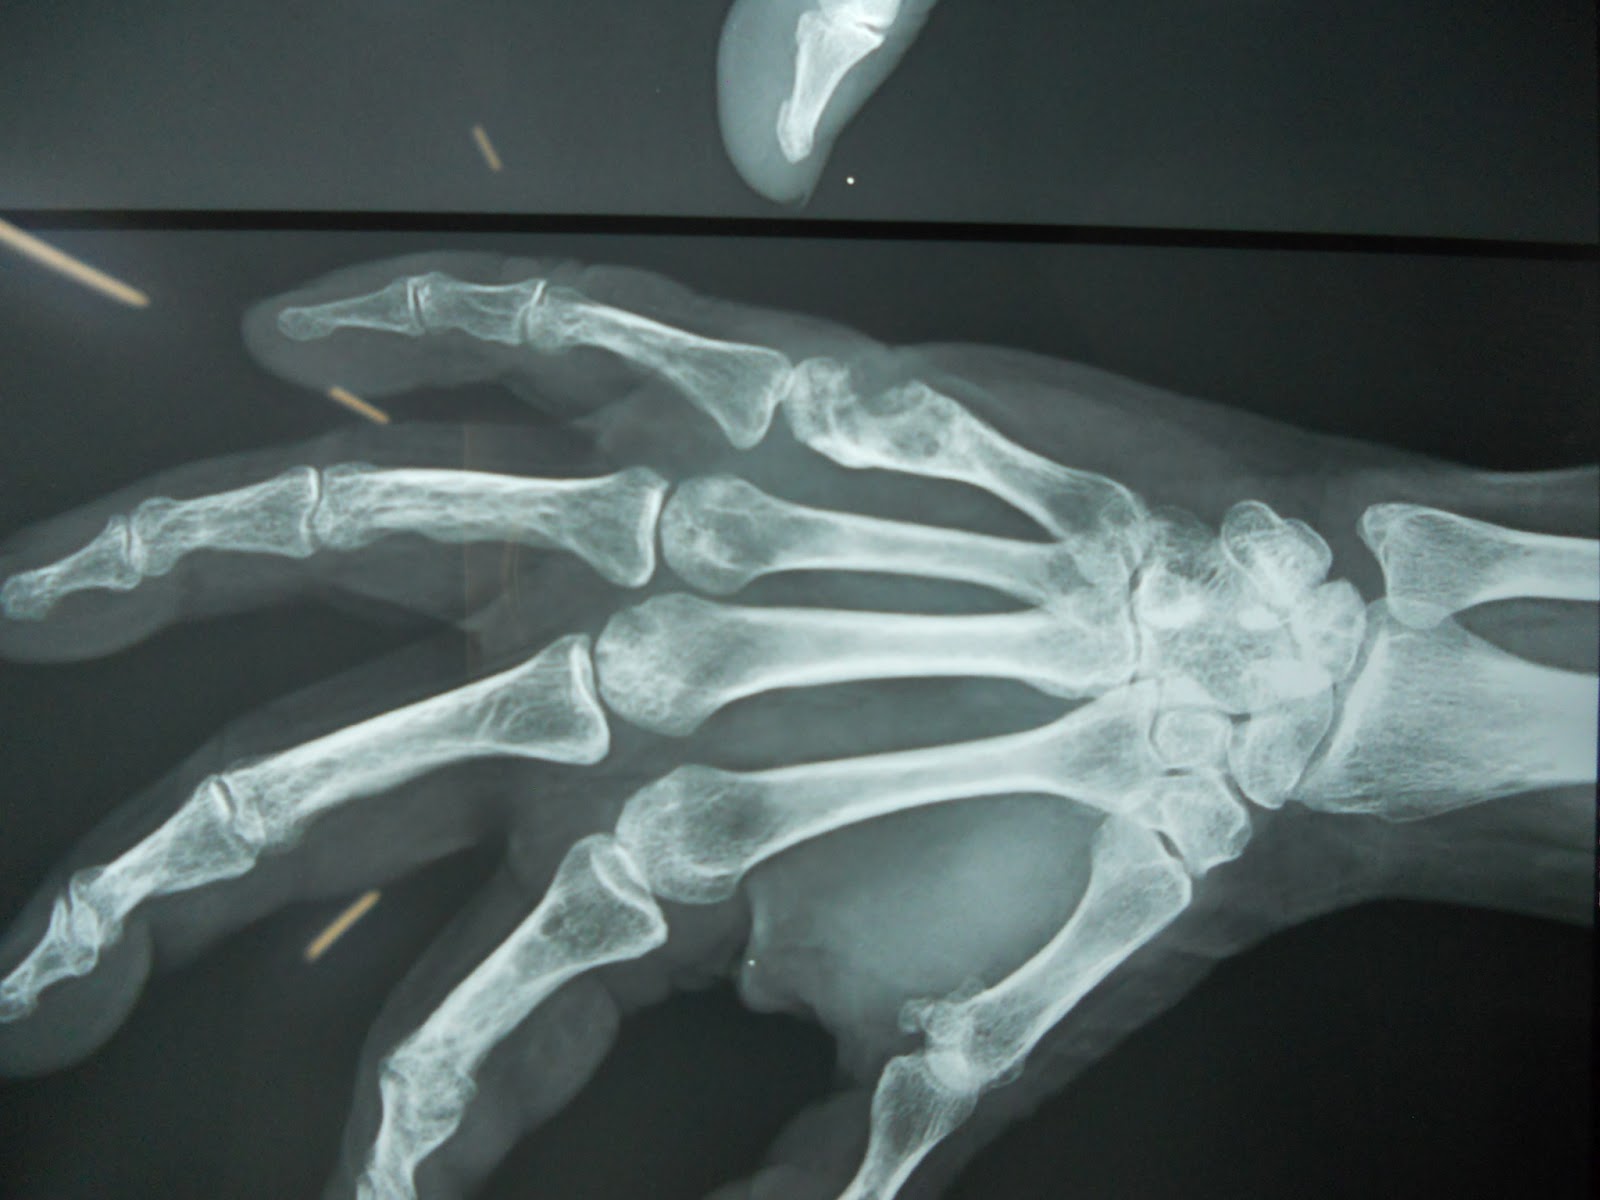
what is the cause for this condition and your plan of management?
a 14 yr old boy came with chief complaints of deformity of rt forearm
h/o trauma 6 years ago..was hit by teacher at school
later he was taken to an outside hospital where the reports suggest he had been operated for compartment syndrome and the operative notes say that they found pockets of pus
o/e
valgus deformity at forearm
midline healed surgical incision
movements are normal except ulnar deviation at wrist
x-ray
Saturday, March 8, 2014
clinical case
a 30 year old male came with chief complaints of pain in hip since 1 year.swelling since 6 months
no relevant trauma
no weight loss
no loss of appetite
O/E: 40 degree of fixed flexion deformity
swelling seen and palpable anteriorly and posteriorly
ROM very painful
what is ur radiological diagnosis
what is ur approach to this case
Friday, October 5, 2012
case 8
A 20 year old female patient presented to our OPD with
complaints of pain in her left foot since about 10 months and
swelling in her left foot since 3 months.
HOPI
Patient was apparently asymptomatic 10 months back when she developed pain in her foot which is insiduos in onset, of dull aching in nature, aggravated by standing and walking, and relieved by taking rest and/or medication. Pain is of increasing severity and is continuous since last 2 months.
Patient developed swelling in her left foot about 3 months back initially diffuse and gradually localized to mid dorsum of foot. There is no history of increase in the size of the swelling.
No h/o trauma
No h/o fever/ weight loss / constitutional symtoms.
No h/o numbness or paraesthesias in the foot.
Past History
No h/o similar complaints i the past.
No h/o TB/ DM/ HTN/ Asthma/ epilepsy/ bleeding disorders.
No h/o past hospitalisation/ surgery
Personal History
Diet mixed
Appetite normal
Sleep disturbed of late due to pain
Family History:
No h/o similar complaints in family members.
No h/o any tuberculous contact.
General examination
20 yr old female who is c/c/c, moderately built and nourished.with pallor,and is without icterus, cyanosis, clubbing, generalized lymphadenopathy, and pedal edema.
Gait antalgic
Vitals stable
other systems normal
Local examination of her left foot
Inspection

Palpation:
Local warmth noted,
Deep tenderness noted over the cuneiform bones and the bases over first second third metatarsal.
Swelling site and size are confirmed,skin over the swelling is pinch able and the swelling is uniformly soft in consistency fluctuant , margins well defined and has minimal mobility in AP and lateral directions. No translucency, neither reducible nor compressible.
Workup and radio graphs attached
MR will be attached shortly
9 months old x rays

Present X rays
Histopathology report of Open biopsy attached
Aspiration yielded straw colored thin fluid which was sterile on microscopy and culture
Open biopsy yielded bits of cheesy material and bony spicules of medial and middle cunieform bones.
What is your clinical radio logical and final diagnosis
how would you like to further manage this patient?
Wednesday, May 23, 2012
clinical case 7
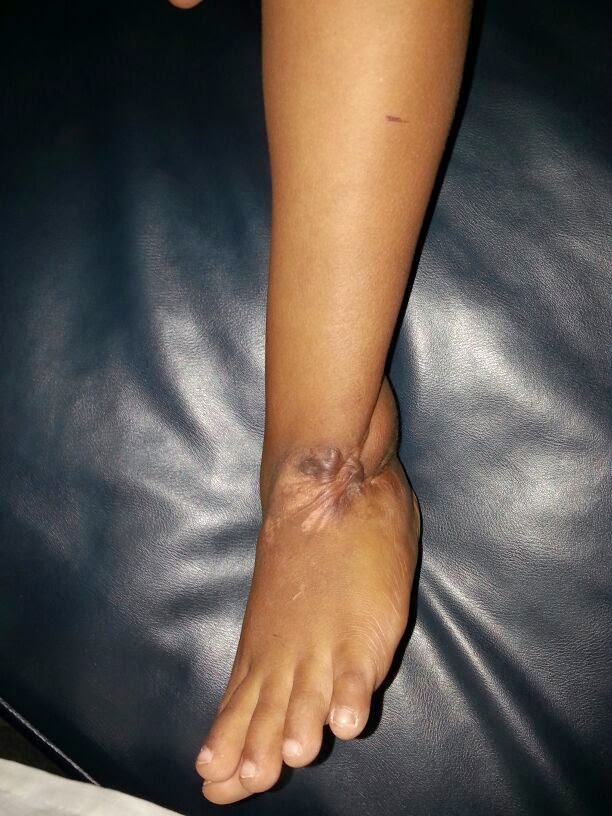
A 3 and half year old child came for review in opd after 2 years for follow up and review...
Child at the age of 1and1/2 yrs developed DVT of her left lower limb following ? DPT vaccination in thigh for which she received parenteral heparin. Following which hematoma developed in left thigh which got infected in due course of illness got converted to abscess with discharging sinus. ! year following the persistent discharging sinus a x ray of left thigh showed features suggestive of COM left femur with sequestrum. The child was treated in this hospital for COM with sequestrectomy and saucerisation.
Now the present x rays and clinical photographs show the remarkable recovery of the child and x ray with hardly any evidence of previous pathology.
Wednesday, May 16, 2012
Friday, March 2, 2012
Case 6
A 9yr old male child was presented by his mother in our
opd with complaints of
pain in the right knee since two years and
difficulty in walking since two years
opd with complaints of
pain in the right knee since two years and
difficulty in walking since two years
HOPI: (Informant is mother)
Pt was apparently alright 2 years back when the
child injured his right knee while playing for which no
medical advice was sought following which child developed
limp and pain while walking
Pain is localized to right knee which is dragging type which
is aggravated by activity and relieved by rest. No history of
radiation.
Mother noticed limp while her child walks and has difficulty
walking and running after the event which is non-progressive.
no h/o similar complaints in family members.
Patient was operated at a local government hospital 4months
back for his condition with no improvement
On General Examination:
A 9 yr old male child who is moderately built and moderately
nourished who is afebrile and is otherwise healthy with
stable vitals
Local examination:
Decubitus:
Pt is lying comfortably on couch with umbilicus central both
ASISs at same level with both hips in neutral position with
apparent wasting in thigh component with right patella facing
the wall left facing the roof both knees in neutral position
and foot plantigrade.
Inspection:
On inspection a surgical healed scar of 5cms long is noted
over the lateral aspect of right knee and a post traumatic
healed scar of 1X1 cm noted in the supero-medial aspect of
right knee. The medial aspect of the knee is more prominent
in comparision to opposite knee. No swellings are noted. No
Parapatellar fossa fullness is noted. Patella appears to be
laterally displaced in comparision to opposite knee. No
sinuses noted.
Palpation:
No local rise of temperature
tenderness is present in the joint line of the right knee and
also elicited in the patellofemoral joint and lateral margin
of patella. Patella is found to be subluxated and its more
mobile laterally compared to opposite knee. The medial
prominence is continuous with the femoral medial condyle
whose size is comparable to the opposte knee. Inspectory
findings of scars and parapatellar fossae are confirmed.
Movements:
patient is having a fixed flexion deformity of 10 degrees
with further full range of flexion active and passive
possible with terminal 10 degrees of flexion painful.
Patient is flexing abducting and external rotating his right
hip to extend the knee and dragging the foot over the crouch
to actively extend his knee.
The patella is dislocating laterally with every flexion of
right knee.
Measurements
The size of the patella is comparable to opposite side. There
is two inches wasting noted in right thigh component.
Gait:
child avoids flexion of knee while walking and running
SPECIAL TESTS Q Angle
Apprehension test is positive as the patient avoids flexion of kneewhen lateral
dislocating pressure is applied over the patella.
Radiological examination:
x rays of right knee AP & Lat suggestive of normal sized
patella with hypoplastic lateral condyle of rt femur. Patella
on axial projections shows flattened lateral n medial
articulate facets with decrease in size of lateral articular
facet. Standing x rays suggestive of horizontal joint line
confirmed.
Insall ratio is around 1.5
Diagnosis:
Recurrent dislocation of Right patella in 9 years old pt.
and suggest the optimal management for the child's
condition.
Subscribe to:
Posts (Atom)